
Silent Reflux (LPR) Symptoms: Why a Normal Scope Doesn't Rule It Out
Short answer: Silent reflux (laryngopharyngeal reflux, or LPR) is reflux that reaches your throat, voice box, and sometimes your nose and ears, often without any heartburn. Symptoms include chronic throat clearing, cough after meals, postnasal drip, a lump-in-the-throat feeling, and hoarseness. There is no gold-standard test for it, so a normal endoscopy does not rule it out. The tissue can start getting support now, before a diagnosis is on paper.
If Your Scope Came Back "Normal" And You Still Feel Terrible
Your endoscopy came back clean. Your bloodwork is fine. You have seen two specialists, and you still clear your throat forty times a day and cough after every meal.
I want to name something up front, because nobody named it for me when I was in the middle of my own reflux: being told everything looks fine when you do not feel fine is invalidating. It makes you question yourself. It makes you wonder if the symptoms are "just allergies," or "just anxiety," or just something you have to live with.
They are usually none of those things. There is currently no gold-standard test for silent reflux, and a normal scope does not rule it out. That one fact explains why so many people arrive at our practice with a folder of normal results and a throat that has not felt normal in years.
So let's walk through what LPR actually looks like, why it behaves differently from GERD, what testing can and cannot tell you, and what we can start doing for your tissue right now.

What Are The Symptoms Of Silent Reflux?
Short answer: Chronic throat clearing, cough (especially after meals), postnasal drip and excess mucus, a globus sensation (the feeling that something is stuck in your throat), hoarseness or voice changes, difficulty taking a full breath, and throat burning. Less recognized symptoms include nasal congestion, nasal and eye burning, and ear pressure.
The classic LPR picture is the one we see every week in the practice: the throat clearing, the cough, the mucus, the lump, the voice that gives out by afternoon.
Then there is the group of symptoms almost nobody connects to reflux: chronic nasal congestion, nasal burning, eye burning, and ear symptoms like Eustachian tube pressure or ringing. A 2026 state-of-the-art review from the leading LPR researchers noted that LPR may show up as posterior nasal inflammation, dry eyes, and middle ear disorders (Lechien et al., 2026, Otolaryngology-Head and Neck Surgery, PMID 42647076, DOI). When refluxate travels high enough to reach the nasopharynx, that tissue reacts the same way your larynx does. It gets irritated, it makes mucus, and it stays that way as long as the exposure continues.
I want to put a number on the nasal piece, because it surprises people. In a 2026 preliminary study, 33 patients with chronic nasal symptoms and no allergy or sinusitis to explain them wore a 24-hour nasopharyngeal pH probe. Reflux reaching the nasopharynx was found in 26 of them, 78.8%, and most of those reflux events were not even acidic. After three months of anti-reflux treatment, their reflux symptom scores and nasal exam findings both improved significantly (Lechien, 2026, Journal of Otolaryngology-Head and Neck Surgery, PMID 42394145, DOI). Small study, no control group, so hold it loosely. But it tells us something encouraging: this tissue is responsive. It can calm down once the exposure stops.
This is also why LPR goes undiagnosed for so long. It looks like allergies. It looks like a sinus problem. It looks like a voice problem. And when the allergy medication does not touch it, most people are simply told to keep taking it.
Silent Reflux Vs GERD: What's The Difference?
Short answer: GERD symptoms are driven mostly by acid contacting the esophagus. LPR symptoms are driven largely by pepsin, the stomach's protein-digesting enzyme, landing on far more delicate throat tissue. You can have LPR without ever having heartburn.
That is the single most important differentiator, and it is why LPR sneaks up on people. Nobody is looking for a reflux diagnosis when they have never had a day of heartburn in their life. Plenty of people have both, but a large group has LPR alone, and if the only advice you have received is GERD advice, you may not be making much progress.
Here is the mechanism behind that gap. In GERD, acid touches the esophagus, so lowering stomach acidity with a PPI (a proton pump inhibitor) can bring real relief. In LPR, the refluxate is often weakly acidic or not acidic at all, and it carries pepsin. When pepsin reaches your larynx, it binds to the tissue and sits there. Your body responds to that irritation by producing mucus to protect you, and the mucus is what drives the throat clearing, the coughing, and the postnasal drip.
Your larynx also has far less protective lining than your esophagus does. That is why these symptoms can feel so intense relative to how "mild" the reflux looks on a test.
Lowering acid does not remove pepsin, and it does not stop reflux from physically moving upward. That is the reason so many people with LPR take a PPI and feel almost nothing change.
Why Is LPR So Hard To Diagnose?
Short answer: There is no gold-standard test. A 2026 review in BMC Gastroenterology states that this is exactly what causes LPR to be both over-diagnosed and under-diagnosed (Treat and Vaezi, 2026, PMID 41612189, DOI). Symptom questionnaires, laryngoscopy, and 24-hour pH-impedance testing each add a piece, and none of them is definitive on its own.
So if your path to answers has felt confusing, that confusion is built into the current state of the science, not into you.
There are still useful tools, and knowing them helps you ask better questions.
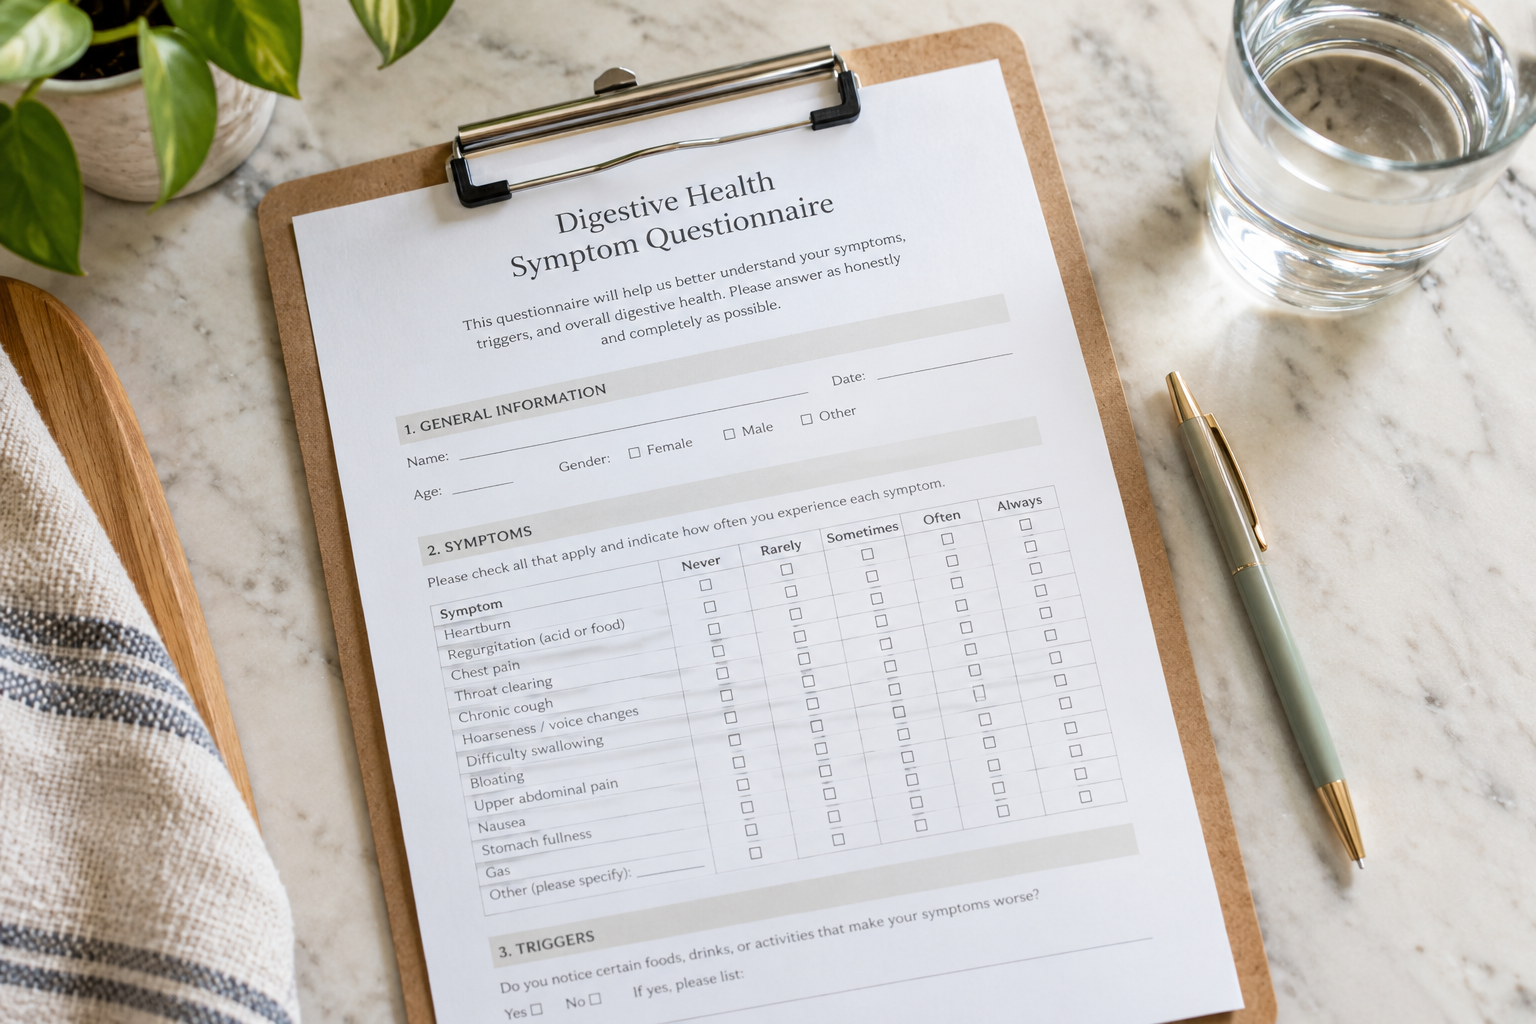
Symptom questionnaires. The Reflux Symptom Index (RSI) is a nine-item questionnaire validated in 2002. In that study, people with LPR scored 21.2 on average, while people without symptoms scored 11.6 (Belafsky et al., 2002, Journal of Voice, PMID 12150380, DOI). A newer, more detailed tool, the Reflux Symptom Score, was validated in 113 LPR patients and 80 controls, and a score above 13 is considered suggestive of LPR-related symptoms (Lechien et al., 2019, The Laryngoscope, PMID 30983002, DOI). Both are available online. Fill one out, bring it to your appointment, and your provider has something concrete to work from.
The right specialist. If your symptoms are primarily in the throat, the specialist you want is a laryngologist, ideally one who is LPR-informed. Many people start with a GI doctor instead, and GI doctors are excellent at the esophagus and stomach, but the larynx is not their area. It is common to be scoped "just in case," have nothing remarkable show up, and leave with a PPI prescription and no explanation.
24-hour pH-impedance testing. This is the best objective test we have right now (sometimes run for 48 hours). It measures your reflux events over a full day: how acidic they are, how high they travel, and whether your symptoms line up with them in time. That last part matters most. If your symptoms do not track with reflux events, or your reflux is within the normal range (some reflux is normal), that points toward other diagnoses that can mimic LPR, like laryngeal hypersensitivity, irritable larynx syndrome, or muscle tension dysphonia. Not every laryngeal symptom is LPR, and a good workup is how we tell the difference.
An empiric PPI trial. This is often the last thing your doctor tries. If it has not worked for you, you are in good company. In the largest placebo-controlled trial of a PPI for reflux-related throat symptoms, esomeprazole 40mg twice daily for 16 weeks resolved the main throat symptom in 14.7% of patients, compared with 16.0% on placebo (Vaezi et al., 2006, The Laryngoscope, PMID 16467715, DOI). PPIs reduce acidity. They do nothing about pepsin or the mechanical movement of reflux upward.
What Can You Do For LPR Before You Have A Diagnosis?
Short answer: Support the barrier that keeps reflux down, reduce how often refluxate reaches the throat, and give the tissue a window to recover. Nutrition and lifestyle are the mainstay of LPR care, and none of it requires a diagnosis on paper to begin.
Until pepsin-deactivating drugs are actually available (they are in development, not on shelves), nutrition and lifestyle are where the leading reflux experts start, and it is where our practice starts, because it is what worked for me and what works for our clients every day.
Your tissue needs support now. These five strategies are what I walk clients through first.
The 3-Hour Buffer. Stop eating three hours before bed (beverages are fine). Build your day around a solid breakfast, a good lunch, an afternoon snack, and a lighter, earlier dinner. This reduces overnight reflux, which matters because lying flat is when refluxate has the most uninterrupted time on your throat tissue.
A temporary low-acid healing phase. Pepsin already sitting in the tissue is switched back on by acid, so a stretch of lower-acid eating gives the tissue time to settle without the enzyme reactivating. This is a healing phase, not a forever list. Then we widen your food list back out on purpose. Mucilaginous herbs like slippery elm helped me through my own healing phase, and they are why I built Sequoia Soothe around 1,000mg of it per serving to soothe irritated tissue.
The LES Lock. One to five minutes of diaphragmatic breathing with 360 ribcage expansion immediately after meals, up to five times a day. Your crural diaphragm wraps around the lower esophageal sphincter, and in a Mayo Clinic randomized controlled trial, LES pressure rose from 23.1 to 42.2 mmHg during the inhale of diaphragmatic breathing and post-meal reflux events fell from 2.60 to 0.36 (Halland et al., 2021, American Journal of Gastroenterology, PMID 33009052, DOI). It is one of the simplest tools we have, and one of the most under-used.
An alginate raft after meals and before bed. Alginates have been used for decades in the UK and Europe and are only recently becoming part of the conversation in the US. An alginate like Reflux Raft, the raft I recommend, forms a gel that floats on top of stomach contents and physically blocks refluxate from moving upward. In a meta-analysis of 14 randomized trials and 2,095 patients, alginates raised the odds of reflux symptom resolution roughly fourfold compared with placebo or antacids (Leiman et al., 2017, Diseases of the Esophagus, PMID 28375448, DOI). For throat symptoms specifically, that mechanical barrier is the point, because less refluxate reaching the larynx means less pepsin landing on it.
Mealtime mindfulness. Chew to applesauce consistency, slow down, and notice your fullness cues so you can end the meal around 80% full. That is hara hachi bu, the Okinawan practice of eating to 80% fullness. A less distended stomach puts less pressure on the barrier, and less pressure means fewer reflux events.
Every one of these is an addition to your healing architecture. We support the barrier. We work with your physiology. Small hinges swing big doors.

Where To Go From Here
If you have spent years assuming your symptoms were allergies that never responded to allergy medication, or you have been told everything looks normal, leave with this: no matter how long this has been going on, there is a path forward for relief.
Pick one thing from the list above and practice it this week. The 3-Hour Buffer is the easiest place to begin. Then, if your symptoms are primarily in your throat, find an LPR-informed laryngologist and bring a completed symptom questionnaire with you.
And if you want someone to walk through your full history and build a personalized nutrition and lifestyle plan, that is exactly what we do in our one-to-one sessions with our expert team of reflux Dietitians. Apply to work with FLORA
You deserve support that actually explains why your body is doing what it's doing. This is the work we do together.
With love,
Molly Pelletier, MS, RD

